
CBG
A non-intoxicating phytocannabinoid often called the “mother cannabinoid” because its acidic form (CBGA) is the biosynthetic precursor of THC, CBD, and CBC in the cannabis plant.
Last updated: 21 September 2026
CBG at a glance
Naturally occurring
Yes
Psychoactive
Psychoactive/non-intoxicating
Cannabinoid type
Phytocannabinoid
Discovery year
1964
Also known as
Cannabigerol, CAS 25654-31-3
Molecular formula
C21H32O2
CB1 receptor interaction
Agonist
CB2 receptor interaction
Agonist
What is CBG?
CBG is a non-intoxicating phytocannabinoid found naturally in Cannabis sativa. It is usually present only in relatively small amounts because much of its acidic precursor CBGA is converted into THCA, CBDA and CBCA as the plant develops. For this reason, CBGA is often described as the central precursor or “mother cannabinoid” of the major cannabinoid families. Some cannabis varieties have been selectively bred to accumulate much higher levels of CBG and CBGA. CBG is also thought to produce more energising and clear-headed effects than many other non-intoxicating cannabinoids.
CBG has a five-carbon (pentyl) side chain and a relatively open, flexible molecular structure compared with cannabinoids such as THC, CBD and CBC. The normal form found in cannabis is (E)-CBG. A much rarer structural form, (Z)-CBG, also exists naturally and is generally known as cannabinerol.
Commercial CBG is generally obtained by extracting and purifying CBG-rich cannabis or hemp, although synthetic and biosynthetic production methods also exist. It is commonly supplied as a high-purity isolate with a strong tendency to crystallise. CBG isolate is typically off-white to beige, with a clumpy powder consistency rather than a liquid distillate.
CBG was first isolated from cannabis resin in 1964, while the central role of CBGA in cannabinoid biosynthesis became clearer during the following decade. It historically received much less attention than THC or CBD, but scientific and commercial interest has increased considerably in recent years. Human research is now emerging, although clinical evidence remains relatively limited.

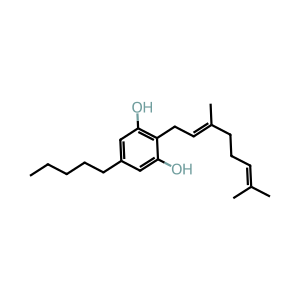
How CBG works in the human body
CBG shows weak activity at CB1 and CB2 but interacts more strongly with several other systems, including alpha2-adrenoceptors, voltage-gated sodium channels, TRP channels, 5-HT1A, PPARα and PPARγ receptors. These mechanisms may contribute to effects involving pain, inflammation, stress responses and metabolism. CBG is also converted into active metabolites including cyclo-CBG.
CB1 receptor
The main cannabinoid receptor in the brain, responsible for THC’s intoxicating effects, binds CBG relatively weakly. One human-receptor study measured a CB1 Ki of 897 nM for CBG versus 35.6 nM for Delta-9-THC under the same conditions, meaning Delta-9-THC showed approximately 25x stronger CB1 binding affinity.
Functional studies indicate weak partial agonist activity, meaning CBG can activate CB1 but much less effectively than Delta-9-THC. Binding and signalling vary considerably between assays. A controlled human study found no meaningful intoxication after oral CBG, consistent with its weak CB1 activity.
CB2 receptor
The main cannabinoid receptor in the immune system, involved in regulating immune cell activity and inflammatory responses. The same receptor study measured a CB2 Ki of 153 nM for CBG versus 8.5 nM for Delta-9-THC, meaning Delta-9-THC showed approximately 18x stronger CB2 binding affinity. CBG nevertheless binds CB2 approximately 5.9x more strongly than CB1.
CBG acts as a partial CB2 agonist, although its strength varies between signalling pathways. CB2 activation could influence immune and inflammatory signalling, but specific CB2-mediated effects have not been established in humans.
Alpha2-adrenoceptor
Alpha2-adrenoceptors help regulate norepinephrine release, which influences alertness, stress responses, heart rate and blood pressure. CBG acted as a potent alpha2-adrenoceptor agonist, with an EC50 of 0.2 nM in a mouse brain signalling assay.
Activation of these receptors normally reduces norepinephrine release, so CBG could potentially influence alertness and reduce physical stress responses such as increased heart rate. This mechanism is well demonstrated experimentally, but its importance in humans has not been established.
Voltage-gated sodium channels
Voltage-gated sodium channels help sensory nerves generate electrical signals, including those involved in transmitting pain. CBG inhibits several of these channels, including NaV1.7 and NaV1.8. Recent human-channel research measured an IC50 of approximately 3.3 µM at NaV1.7 and 0.9 µM at NaV1.8, showing particularly strong inhibition of NaV1.8.
Inhibiting these channels can make pain-sensing nerves less likely to become activated and transmit repeated pain signals. This could potentially contribute to reduced pain sensitivity and less persistent pain signalling, although these effects have not yet been confirmed clinically in humans.
TRP ion channels
TRP channels help sensory nerves detect temperature, irritation and pain-related signals. CBG activates TRPA1 at approximately 0.7 µM, TRPV1 at 1.3 µM and TRPV2 at 1.7 µM, followed by desensitisation. CBG also activates TRPV3 and TRPV4 at low concentrations.
CBG additionally blocks the cold-sensing TRPM8 channel with an IC50 of approximately 0.16 µM.
Together, these interactions could influence pain, temperature sensitivity and inflammatory responses, although their contribution to CBG’s effects in humans remains uncertain.
5-HT1A receptor
The 5-HT1A receptor helps regulate serotonin signalling involved in mood, stress and emotional processing. CBG acts as a 5-HT1A antagonist, with an apparent KB of 51.9 nM in animal brain tissue. This means it reduces activation caused by other molecules at this receptor rather than activating it itself.
Blocking 5-HT1A can have different effects depending on where the receptor is located. It may increase serotonin release in some brain areas, while also reducing some of serotonin’s calming effects elsewhere. CBG could therefore potentially influence mood, anxiety and stress responses, although its actual effects through this mechanism in humans remain unknown.
PPARα and PPARγ receptors
PPARα and PPARγ are receptors that regulate gene activity involved in inflammation, fat metabolism and energy balance. Experimental research identifies CBG as a dual PPARα and PPARγ agonist, meaning it can activate both receptors.
Activating PPARα can increase the breakdown and use of fats for energy, while PPARγ can influence fat storage and how cells respond to insulin. Activation of both receptors can also reduce some inflammatory activity. CBG could therefore potentially affect inflammation, fat metabolism and blood-sugar regulation, although these effects have not been established in humans.
Anandamide uptake
Anandamide is an endocannabinoid naturally produced by the body that helps regulate pain, mood, stress and other cannabinoid-related processes. CBG inhibits the cellular uptake of anandamide, with a reported Ki of approximately 11.3 µM.
By slowing anandamide uptake into cells, CBG could keep it active for longer and strengthen its effects. This may potentially contribute to reduced pain perception, changes in mood and lower stress responses, although these effects have not been established in humans.
Metabolism
After oral administration, CBG is absorbed into human blood. In laboratory research using human liver enzymes, CBG is rapidly converted into several metabolites. The main identified metabolite is cyclo-CBG, while 6′,7′-epoxy-CBG is formed in much smaller amounts. Cyclo-CBG was produced approximately 100 times more than 6′,7′-epoxy-CBG under the tested conditions.
Human enzymes contribute to this metabolism. Both metabolites have shown biological activity in laboratory cell research, including effects on inflammatory responses, although their contribution to CBG’s effects in humans remains unknown.
✓
Human safety status
No short term harm found, long term data not yet established
Controlled human studies include single-dose exposure and four weeks of repeated oral CBG. A 20 mg study found no meaningful intoxication or impairment. In a four-week trial, 33 participants received 25 mg followed by 50 mg CBG daily, while 30 received placebo. Five participants each reported one different mild side effect: headache, lethargy, stomach upset, nausea or excessive sleepiness. Because none of these effects occurred more than once, it remains uncertain whether they were caused by CBG. No serious CBG-related adverse events were reported.
CBG interactions with other compounds
CBG can interact with other cannabinoids, common substances and medicines by changing their metabolism, blood exposure or biological effects. These interactions may increase, decrease or modify the effects of either compound, and can sometimes change how long those effects remain active in the body. Their strength and relevance can vary substantially depending on the specific combination, dose and route of administration.
Important disclaimer
This information is provided for educational and technical reference only. Interaction data can change as new research becomes available and may be incomplete or outdated. The real relevance of any interaction depends strongly on dose, route of administration, timing, formulation and individual metabolism. Readers should do their own research and consult a qualified healthcare professional before making decisions involving medicines, alcohol, nicotine, cannabinoids or other compounds. Elementra's products and information are intended for research, production and technical use only and are not intended for human consumption.
Medicines
Capsaicin
Cell study
Capsaicin-induced nerve signalling decreases
CBG directly reduced the response of sensory neurons to capsaicin in laboratory testing. The effect increased with higher CBG concentrations, with the strongest inhibition observed at 30 µM CBG. This suggests that CBG can weaken capsaicin-related pain signalling, but the interaction has not yet been confirmed in humans.
Tolbutamide
Enzyme study
Tolbutamide blood exposure may increase
CBG strongly inhibits CYP2C9-mediated metabolism of tolbutamide in laboratory testing, with an inhibitory concentration of about 1.0 µM. By slowing the breakdown of tolbutamide, CBG could cause more of the medicine to remain in the bloodstream, potentially increasing or prolonging its glucose-lowering effect. The resulting increase in blood exposure has not yet been measured or confirmed in humans.
Warfarin
Potential
Warfarin blood exposure may increase
CBG inhibits CYP2C9, the main enzyme responsible for breaking down S-warfarin, the more potent form of warfarin. By slowing this clearance, CBG could increase warfarin blood exposure and strengthen its anticoagulant effect, potentially increasing bleeding risk. This interaction is pharmacologically plausible but has not been directly demonstrated with CBG in humans.
Phenytoin
Potential
Phenytoin blood exposure may increase
Phenytoin is substantially metabolized by CYP2C9, which CBG inhibits in laboratory testing. CBG could therefore slow phenytoin clearance and increase its blood concentration. This may be especially relevant because phenytoin has a narrow therapeutic range, but the interaction has not yet been directly confirmed with CBG in humans.
Related terms
Educational information only
This content does not constitute advice
All information in the Cannabinoid Knowledge Hub is provided solely for educational and scientific purposes. It does not constitute medical advice, usage advice, dosage guidance or instructions for mixing, combining or consuming substances.
Discussions of effects, interactions and risks are descriptive only and should not be interpreted as a recommendation or encouragement to use or combine any substance. Visitors are responsible for complying with all applicable laws and regulations in their country or jurisdiction. Nothing in the Knowledge Hub may be used to support illegal activity.
Read the full disclaimer